
CJ Henley, DMD, PA / San Marco, Jacksonville, Florida
Oral cancer screening in Jacksonville, FL.
Warning signs, the exam, and what happens next.
An oral cancer screening is a careful look at and feel of your lips, mouth, throat, and neck for changes that could be cancer or precancer. At our San Marco office it is part of every exam, for every patient. Most spots we find are harmless; when one isn’t clearly harmless, Dr. CJ Henley, who serves on the Head & Neck Tumor Board at Baptist MD Anderson, gives you a clear plan: recheck, biopsy, or referral.
- 60,480new mouth and throat cancers expected in the U.S. in 20261
- 26%of oral cavity and pharynx cancers are found while still localized2
- 88.7%five-year relative survival when localized, vs 36.0% once it has spread to distant sites2
- 2 weeksa sore, patch, or lump that lasts longer than this needs an exam14
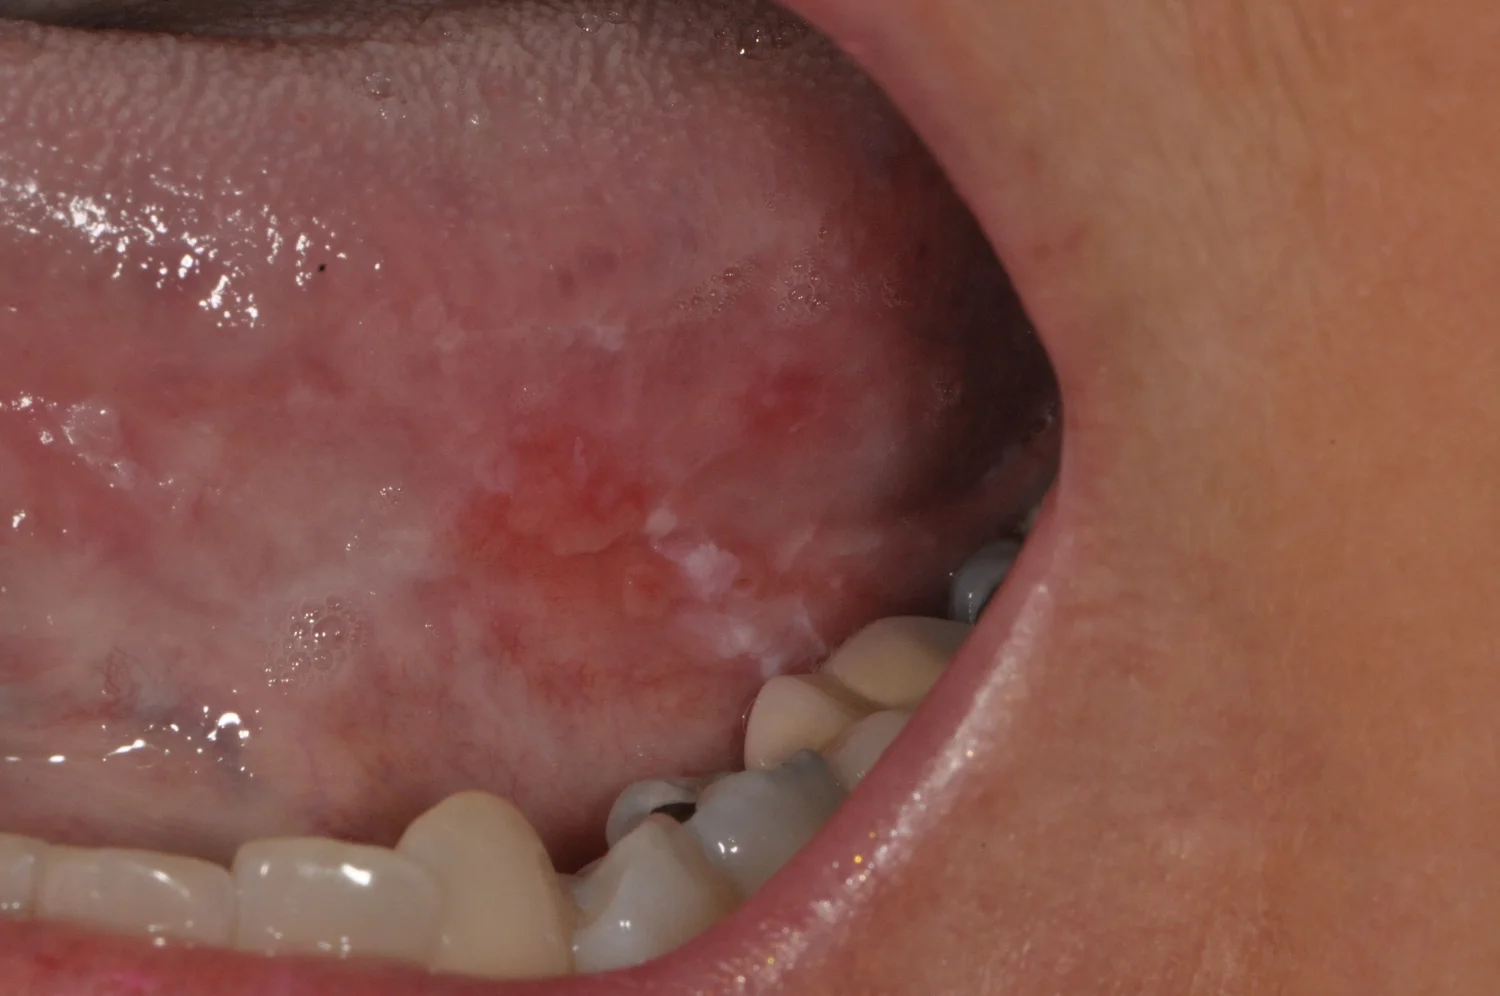
What is an oral cancer screening?
What an oral cancer screening is, and what it isn’t.
An oral cancer screening is a visual and hands-on exam of the lips, mouth, visible throat, and neck that looks for changes that could be cancer or precancer. It finds and sorts spots; it doesn’t diagnose cancer. Only a biopsy can do that.
“Oral cancer” usually means two related cancers: oral cavity cancer (lips, tongue, cheeks, gums, floor and roof of the mouth) and oropharyngeal cancer (the back of the tongue, tonsils, and throat). Oral cavity cancer is mostly linked to tobacco and alcohol; oropharyngeal cancer is now mostly linked to HPV.14,19
At our Jacksonville office, oral cancer screening isn’t an add-on. It is part of every comprehensive exam and every checkup, for every patient, whether or not you smoke or drink. The American Dental Association’s 2026 guideline says every adult should have a clinical oral exam.6,7 It takes a few minutes, needs no preparation, and doesn’t hurt.
Dr. CJ Henley is a general dentist with advanced training in oral medicine, the area of dentistry that diagnoses diseases of the mouth’s lining, and serves on the Head & Neck Tumor Board at Baptist MD Anderson. That background shapes how carefully we look and how quickly we act when something doesn’t fit.
The oral cancer exam
What happens during your oral cancer screening.
Dr. Henley reviews your risk factors, feels your face, jaw, and neck for lumps and lymph nodes, then examines every surface inside your mouth, including the sides and underside of the tongue. Anything worth watching is photographed and measured, and you hear the results before you leave.
History and risk review
Tobacco, vaping, alcohol, sun exposure, prior cancer, medications, and any change you’ve noticed, such as a sore, a numb spot, or a denture that suddenly doesn’t fit.
Face, lips, jaw, and neck
A hands-on exam of the lymph nodes under the jaw and along the neck, the salivary glands, and the lips, looking for lumps, firmness, or tenderness.
Inside the mouth
Cheeks, gums, the roof and floor of the mouth, and the tongue, held gently with gauze so the sides and underside can be seen and felt. Then the visible throat and tonsils.
Photos and measurements
Any lesion worth monitoring is photographed and measured, so a change is judged against a record, not memory.
Results and a plan
Usually: “everything looks healthy.” Otherwise you leave with a specific next step and a date. See if we find something.
Bring any removable dentures or retainers; we look under them too. No light, dye, or rinse is needed; here’s why.
Signs of oral cancer
Signs of oral cancer and mouth cancer, and when to worry.
The early signs of mouth cancer are a sore that doesn’t heal, a white or red patch, or a lump or thickening, and they are often painless. Any of these lasting more than two weeks should be examined, even if your next checkup is months away.
On the tongue, cheek, gums, and floor of the mouth
The sides and underside of the tongue and the floor of the mouth are the most common sites for oral cavity cancer.1 Inside the cheek, watch for a patch or sore that doesn’t match a bite or a sharp tooth. Gum cancer can look like a sore or overgrowth that doesn’t act like gum disease. Our post on the warning signs of mouth cancer covers what to look for.
On the lips, and the Florida sun
Lip cancer usually starts on the lower lip, where the sun hits, as a scaly patch, a crust that keeps coming back, or a sore that won’t heal. Boaters, fishermen, golfers, and anyone who works outdoors in Jacksonville should wear an SPF lip balm and show us any lip change that lasts.
a sore, white or red patch, lump, or numb area in your mouth lasts more than two weeks, or you find a firm, painless lump in your neck. You don’t need to wait for your next checkup. Call us at 904.398.1549; for trouble breathing or swallowing, go to an emergency department. See emergency dental care.
Precancerous lesions
White and red patches: what “precancerous” really means.
Some mouth patches, or lesions, are called potentially malignant disorders: most never become cancer, but they carry a higher risk than normal tissue. A white patch (leukoplakia) turned into cancer in about 1 in 10 cases in pooled studies; a red patch (erythroplakia) in about 1 in 3. That’s why we photograph, recheck, and biopsy them.
Leukoplakia: a white patch
A white patch that won’t wipe off and has no other explanation. In pooled studies, about 9.5% to 9.8% became cancer over time, with a wide range between studies.10,11 Patches that are speckled or uneven, on the tongue or floor of the mouth, or show dysplasia on biopsy carry more risk.
Erythroplakia: a red patch
A velvety red patch with no other cause. Rarer than leukoplakia but more serious: about a third became cancer in pooled studies.10 A red patch that persists is biopsied, not watched.
Proliferative verrucous leukoplakia
A slowly spreading, warty white condition, often in older women who never smoked. About half of cases became cancer in pooled studies, so it needs long-term follow-up.10
Oral lichen planus
A common inflammatory condition with lacy white lines, sometimes sore. Its cancer risk is low, about 0.4% to 1.4% depending on how strictly it is diagnosed,12,13 but it deserves regular checks. See oral lichen planus.
“Potentially malignant” is the term the World Health Organization’s collaborating centre uses for these conditions.18 It means “watch closely,” not “you have cancer.” Dysplasia, abnormal cells on a biopsy, is graded mild, moderate, or severe; moderate or severe dysplasia roughly doubled the odds of cancer compared with mild.10 A white coating that does wipe off is usually something else; see causes of a white tongue.
Found a lump?
Found a lump or spot? It’s often something harmless.
Most lumps and spots in the mouth are benign: a bony torus, a bite fibroma, a mucous cyst, or a canker sore. An exam is the fastest way to know, and the reason to come in is that you can’t tell them apart reliably at home.
Torus: a bony bump
A hard, smooth bony growth in the middle of the roof of the mouth or inside the lower jaw. It has usually been there for years. Read about torus palatinus.
Fibroma: a bite bump
A firm, smooth, pink lump on the cheek, lip, or tongue where you bite. Benign, but removed and checked if it grows or bothers you.
Mucocele and canker sores
A soft, bluish bubble on the lower lip from a blocked salivary gland; or a painful ulcer that heals in one to two weeks. A sore that outlasts two weeks gets an exam.
Cheek-bite lines, geographic tongue
White lines or shaggy patches where you chew your cheek, and map-like patches on the tongue that move around. Usually harmless; dry mouth and burning can also change how the mouth looks and feels (see dry mouth and burning mouth syndrome).
Oral cancer risk factors
Who is at higher risk for oral cancer.
Tobacco, heavy alcohol use, HPV, sun on the lips, older age, and a prior head and neck cancer raise the risk of oral cancer. Tobacco and alcohol together are worse than either alone. But oral cancer also occurs in people with no risk factors, which is why we screen everyone.
HPV and oral cancer
HPV and throat cancer: what a dental exam can and can’t see.
Most throat (oropharyngeal) cancers in the U.S. are now caused by HPV. They start in the tonsils and the base of the tongue, which are partly hidden from a dental exam, so symptoms matter as much as the screening. A one-sided sore throat, ear pain, or neck lump that lasts should be checked by an ENT.
In U.S. tumor samples, the share of oropharyngeal cancers linked to HPV rose from about 16% in the 1980s to about 72% by the early 2000s.16 HPV-related throat cancer often affects people who never smoked, and it is often found as a painless lump in the neck rather than a sore in the mouth.
During your oral cancer screening we look at the visible throat and tonsils and feel the neck, but no dental exam can see the base of the tongue or deep in the tonsils, and no screening light or rinse changes that. If you have any of these for more than two to three weeks, tell us, and see your physician or an ENT:
- A sore throat or ear pain on one side
- A lump in the neck
- Pain or difficulty swallowing, or a feeling that something is stuck
- Hoarseness or a voice change
HPV vaccination is recommended for children at ages 11 to 12 and can be given through age 26; adults older than that can ask their doctor whether it makes sense for them.19
How often
Who should have an oral cancer screening, and how often.
Every adult should have an oral cancer exam as part of regular dental care, and here that happens at every exam and checkup. People at higher risk, people with a spot being watched, and cancer survivors are checked on a closer schedule.
Published advice varies, from yearly screening for adults to every few years for younger, low-risk adults. We don’t make you choose: the exam takes a few minutes, so it is built into every visit. If we are watching a patch, we set a specific recheck date; survivors are checked on a schedule coordinated with their oncology team.
The honest evidence
What oral cancer screening can and can’t do, and why we don’t use a screening light.
A careful oral exam is good at ruling out disease, and the American Dental Association’s 2026 guideline recommends one for every adult. The same guideline recommends against routinely adding screening lights, dyes, or brush tests, because they flag many harmless spots and can’t replace a biopsy.
The evidence on mass screening is honest about its limits. The U.S. Preventive Services Task Force found it couldn’t judge the benefit of oral cancer screening by primary care doctors in people without symptoms.3 The one large trial, in India, found no significant drop in deaths overall, but a 24% drop among people who used tobacco or alcohol, the group at highest risk.4,5 A 2021 Cochrane review found a conventional oral exam was very good at correctly clearing healthy mouths (specificity 94% to 99%), with variable sensitivity, and urged dentists to stay vigilant.8
| Tool | What it does | What the evidence says | How we use it |
|---|---|---|---|
| Visual and hands-on exam | Looks at and feels every surface and the neck | ✓ Recommended for all adults6,7 | Every exam, every patient |
| Screening light (e.g. VELscope, OralID) | Tissue glow under a special light | ✗ Recommended against for routine use; flags many harmless spots (specificity about 50%)6,9 | Not used |
| Dye (toluidine blue) | Stains suspicious tissue | ✗ Recommended against, very low certainty21 | Not used |
| Brush biopsy (cytology) | Collects surface cells with a brush | Not for routine use; reserved for when a scalpel biopsy isn’t possible or indicated7 | Selected cases only |
| Saliva tests | Looks for markers in saliva | Research use only20 | Not used |
| Biopsy | Removes a small piece of tissue for a pathologist | ✓ The reference standard; the only way to diagnose6,9 | In office, or by referral |
Some offices advertise a light or “laser” screening as more advanced. The research doesn’t support it: lights don’t find cancers a careful exam misses, and the false alarms lead to worry and extra visits. We rely on a thorough hands-on exam, photographs over time, and a biopsy when a change persists.
After a finding
If we find something: the plan and the timeline.
Most findings need only a recheck. We photograph and measure the spot, remove any obvious irritant such as a sharp tooth or denture edge, and look again in about two weeks. If it hasn’t resolved, Dr. Henley performs a biopsy in the office or refers you to the right surgeon, and he stays involved.
01 Record
Photo and measure
The spot is photographed and measured, and likely causes are noted.
02 Recheck
About two weeks
Irritants are removed; many ulcers and patches clear on their own by the recheck.
03 Biopsy
If it persists
A small biopsy in our office, sent to a pathology lab, or a brush biopsy in selected cases.
04 Refer
If needed, fast
To an oral and maxillofacial surgeon, an ENT, or the Baptist MD Anderson head and neck team.
Why wait two weeks, not biopsy today?
Many sores and patches are caused by a sharp tooth, a denture, or a bite, and heal within a week or two once the cause is gone.19 A recheck avoids unnecessary biopsies. That doesn’t apply to everything: a red patch, a firm or fixed lump, or anything that looks clearly suspicious is biopsied, or we refer you, without waiting.
What a biopsy is like
The area is numbed, a small piece of tissue is removed, and the site is usually closed with a stitch or two. Most people take an over-the-counter pain reliever for a day or two. The pathologist’s report usually comes back within about a week or two, and we go over it with you directly. A brush biopsy is quicker but isn’t a substitute for a scalpel biopsy of a suspicious lesion.7
Is oral cancer curable?
Is oral cancer curable? Why the stage at diagnosis matters.
Oral cancer is often curable when it is found early. Five-year relative survival is about 89% when it is still localized, but about 36% once it has spread to distant sites. Only about a quarter of cases are found at the localized stage, which is the reason to look carefully and act on persistent changes.
| Stage at diagnosis | Share of cases | Five-year relative survival |
|---|---|---|
| Localized (confined to where it started) | 26% | 88.7% |
| Regional (spread to nearby lymph nodes or tissue) | 55% | 69.7% |
| Distant (spread to other parts of the body) | 12% | 36.0% |
| All stages | — | 69.9% |
These are population averages, not predictions for any one person. Survival also depends on the site, the cancer’s type and HPV status, overall health, and treatment.
If you’re diagnosed
If you’re diagnosed: tumor-board coordination and dental care before treatment.
If cancer is diagnosed, your mouth needs to be ready before radiation or chemotherapy, ideally about a month before treatment starts. Dr. Henley serves on the Head & Neck Tumor Board at Baptist MD Anderson and coordinates dental care in Jacksonville with your surgeons and oncologists before, during, and after treatment.
The National Institute of Dental and Craniofacial Research advises seeing a dentist about one month before cancer treatment, if possible, so infected or failing teeth can be treated and the mouth can heal before radiation.14 That planning lowers the risk of bone and jaw complications later.
- Before treatment: a full exam and X-rays, treatment of problem teeth, and custom fluoride trays. See dental care for head and neck cancer.
- During treatment: managing dry mouth, sores, and infections; see cancer and dental health.
- After treatment: jaw stiffness (radiation-induced trismus), replacing missing tissue with an obturator after maxillectomy, and lifelong checks for new changes.
Physicians and oncology teams can use our physician referral information to coordinate care.
Between visits
How to check your own mouth once a month.
A monthly self-exam with a bright light and a mirror helps you notice a change sooner. It doesn’t replace a professional oral cancer screening, and the evidence for self-exams alone is limited,8 but it tells you when not to wait.
01 Lips
Lips and cheeks
Pull your lips out and cheeks aside; look for patches, sores, or lumps.
02 Tongue
Sides and underside
Hold the tip with gauze, move it side to side, then lift it to see underneath.
03 Roof and floor
Roof and floor
Tilt your head back for the roof; lift the tongue for the floor of the mouth.
04 Neck
Feel the neck
Feel under the jaw and down both sides of the neck for new lumps.
Cost and insurance
Does insurance cover an oral cancer screening?
At our Jacksonville office, oral cancer screening is part of your comprehensive exam and checkups, not a separate charge. If a biopsy is needed, the procedure and the pathology lab’s report are separate, and we explain the fees before anything is done.
The pathology lab that reads a biopsy may bill you or your insurance directly. We are an out-of-network practice. Some dental plans cover exams and biopsies, often with a frequency limit. We can help you understand how to use your benefits; you are responsible for amounts your plan does not pay. Call our team with your plan details to ask about fees and payment arrangements. Read what patients should know about out-of-network dental insurance.

Oral cancer screening near you
Oral cancer screening in San Marco, for all of Jacksonville.
Dr. CJ Henley is a general dentist with advanced training in oral medicine who serves on the Head & Neck Tumor Board at Baptist MD Anderson. He examines every patient himself, and he sees patients during and after head and neck cancer treatment, which is why a spot that doesn’t fit gets a decision, not a shrug. Patients come to our San Marco office for oral cancer screening in Jacksonville and from across Northeast Florida.
If you’ve noticed a change, you don’t need to wait for a routine checkup. Call to book an exam, read our reviews, learn about our San Marco dental office, or start with our new-patient forms. Patients in Mandarin and Southside can also read our Mandarin and Southside and Baymeadows pages.
San Marco
On Hendricks Avenue, in the neighborhood
A recheck visit fits into a lunch hour.
Downtown and Southbank
Southbank borders us; Downtown is across the Main Street Bridge
Easy to fit an exam around a workday.
Riverside, Avondale, and Ortega
Across the St. Johns River on the Fuller Warren Bridge
A short trip for a careful oral cancer exam.
San Jose and Mandarin
North on San Jose Boulevard, which becomes Hendricks Avenue
One road from Mandarin to our door.
Southside and Baymeadows
North on I-95 from Baymeadows Road
A quick drive when a spot needs a second look.
Jacksonville Beach, Neptune Beach, and Atlantic Beach
West on Atlantic Boulevard or Beach Boulevard
Lip checks matter most where the sun is strongest.
Ponte Vedra and Nocatee
West on J. Turner Butler Boulevard, then north on I-95
Rechecks are scheduled ahead so you make one trip at a time.
Orange Park and Fleming Island
North on US-17 to I-95, then across the Fuller Warren Bridge
Visits booked ahead to plan around work.
St. Augustine
North on I-95
Worth the drive for coordination with the Baptist MD Anderson head and neck team.
Frequently asked questions
Questions about oral cancer screening.
What is an oral cancer screening?
An oral cancer screening is an exam of your lips, mouth, visible throat, and neck that looks and feels for changes that could be cancer or precancer, such as a sore that won’t heal, a white or red patch, or a lump. It doesn’t diagnose cancer; a biopsy does. At our office it is part of every exam.
What does the dentist check during an oral cancer exam?
Your risk factors and any changes you’ve noticed; the lymph nodes under your jaw and along your neck; your lips, cheeks, gums, and the roof and floor of your mouth; your tongue, including its sides and underside; and the visible throat and tonsils. Anything worth watching is photographed and measured.
How long does an oral cancer screening take, and does it hurt?
A few minutes, and it doesn’t hurt. You may feel gentle pressure on your neck and jaw and a gauze pad holding your tongue. There is nothing to prepare; just bring any removable dentures or retainers so we can look underneath.
How often should I have an oral cancer screening?
At every dental exam or checkup, which for most people is once or twice a year. That’s how we do it here. People at higher risk, people with a patch being watched, and cancer survivors are checked on a closer schedule. Don’t wait for a checkup if a change lasts more than two weeks.
Do I need an oral cancer screening if I don’t smoke or drink?
Yes. Tobacco and alcohol raise the risk, but oral cancer also occurs in people who never smoked, including HPV-related throat cancer and a rise in tongue cancer among younger adults. That’s why we screen every patient.
What are the early signs of mouth cancer?
The early signs of mouth cancer are a sore or ulcer that doesn’t heal in two weeks; a white or red patch that won’t wipe off; a lump, thickening, or rough spot; numbness of the tongue or lip; and trouble chewing or swallowing. Early mouth cancer is often painless, so don’t wait for pain.
Is a white patch on my tongue cancer?
Usually not. A white coating that wipes off is often harmless. A white patch that won’t wipe off and has no other cause is called leukoplakia; most never become cancer, but about 1 in 10 did in pooled studies, so it should be examined, photographed, and often biopsied.
Why is a red patch in the mouth more concerning than a white one?
A persistent red patch with no other cause, called erythroplakia, is less common than a white patch but about a third became cancer in pooled studies. A red or speckled red-and-white patch that lasts should be biopsied rather than watched.
I have a sore in my mouth that won’t heal. When should I worry?
If it has lasted more than two weeks. Most mouth sores, including canker sores and bite injuries, heal within one to two weeks. A sore that outlasts that, especially a painless or firm one, should be examined; you don’t need to wait for your next checkup.
I found a lump on my gum, cheek, or the roof of my mouth. Is it cancer?
Most often, no. Common harmless lumps include a bony torus on the roof of the mouth, a fibroma where you bite your cheek, and a mucous cyst on the lip. But you can’t reliably tell them apart at home, so a new lump, or one that is growing, firm, or fixed, should be examined.
Can oral cancer appear on the lips?
Yes. Lip cancer usually appears on the lower lip as a scaly patch, a crust that keeps coming back, or a sore that won’t heal, and sun exposure is the main risk. In sunny Jacksonville, use an SPF lip balm and show us any lip change that lasts.
Can a dentist find HPV-related throat cancer?
Only partly. We examine the visible throat and tonsils and feel the neck, but HPV-related cancers often start at the base of the tongue or deep in the tonsils, where no dental exam can see. A one-sided sore throat, ear pain, a neck lump, or trouble swallowing lasting more than two to three weeks should be checked by a physician or ENT.
Does vaping cause mouth cancer?
No one knows yet. E-cigarettes haven’t been used long enough for long-term cancer data, so they can’t be called safe for the mouth. We advise quitting, and we examine people who vape as carefully as people who smoke.
Why is tongue cancer showing up in younger people who never smoked?
Researchers don’t know yet. U.S. data show oral tongue cancer rising in adults under 50, including people with no tobacco or alcohol use, and the rise isn’t explained by HPV. It’s one more reason we screen every patient, regardless of age or habits.
Do you use a screening light like VELscope or OralID?
No. The American Dental Association’s 2026 guideline recommends against routinely adding screening lights, because they flag many harmless spots and can’t replace a biopsy. We rely on a careful hands-on exam, photographs over time, and a biopsy when a change persists.
Does oral cancer screening actually save lives?
For people at higher risk, the best evidence suggests it can. One large trial found a 24% reduction in oral cancer deaths among tobacco and alcohol users who were screened, but no significant drop overall. Finding cancer at an earlier stage clearly matters: five-year survival is much higher when it is localized.
What happens if you find something suspicious?
We photograph and measure it, remove any irritant, and usually recheck in about two weeks. If it persists, Dr. Henley performs a biopsy in the office or we refer you to an oral and maxillofacial surgeon, an ENT, or the Baptist MD Anderson head and neck team. A red patch or a clearly suspicious lump isn’t watched; it is biopsied or referred right away.
What is a biopsy, and do you do it in the office?
A biopsy removes a small piece of tissue, under local anesthetic, so a pathologist can look at it under a microscope. It is the only way to diagnose oral cancer or precancer. Dr. Henley performs biopsies in our office, and we refer you when a surgeon is the better choice. A brush biopsy is used only in selected cases.
Is oral cancer curable if it’s caught early?
Often, yes. In U.S. data, five-year relative survival is about 89% when oral cavity and pharynx cancer is found while still localized, compared with about 36% once it has spread to distant sites. Only about a quarter of cases are found that early.
How can I check my own mouth at home?
Once a month, with a bright light and a mirror: look at your lips and cheeks, hold your tongue with gauze to see its sides and underside, check the roof and floor of your mouth, and feel under your jaw and along your neck. A self-exam supplements, not replaces, a professional oral cancer screening.
Does insurance cover an oral cancer screening?
At our office the screening is part of your comprehensive exam and checkups, so there is no separate screening fee. A biopsy and the lab’s report are separate. We are an out-of-network practice and can help you understand how to use your benefits. Call our team with your plan details to ask about fees before scheduling.
Where can I get an oral cancer screening in Jacksonville?
CJ Henley, DMD, PA provides oral cancer screening at 3675 Hendricks Avenue, Jacksonville, FL 32207, in San Marco, as part of every exam. Patients come from Mandarin, Southside, Riverside, the Beaches, Ponte Vedra, Orange Park, and St. Augustine. Call 904.398.1549, and tell us if you’ve noticed a change so we can see you sooner.
More reading: Warning signs of mouth cancer · Oral Cancer Awareness Month · Dental FAQ
Your next step
Noticed a change? Don’t wait for your checkup.
If a sore, patch, or lump has lasted more than two weeks, call our Jacksonville office for an exam. If it’s simply time for a checkup, your oral cancer screening is included. If you have trouble breathing or swallowing, or a facial injury, see emergency dental care.
CJ Henley, DMD, PA3675 Hendricks Avenue
Jacksonville, FL 32207
Prefer a nonurgent text? 904.762.5616 is our practice on-call and text line. Please don’t send sensitive health information by text, and call for anything urgent.
Related pages
Sources
- American Cancer Society. Key statistics for oral cavity and oropharyngeal cancers. Revised 2026. See also Siegel RL, et al. Cancer statistics, 2026. CA Cancer J Clin. 2026;76(1):e70043.
- National Cancer Institute. SEER Cancer Stat Facts: Oral cavity and pharynx cancer. Accessed October 2026.
- Moyer VA; U.S. Preventive Services Task Force. Screening for oral cancer: U.S. Preventive Services Task Force recommendation statement. Ann Intern Med. 2014;160(1):55-60.
- Brocklehurst P, Kujan O, O’Malley LA, Ogden G, Shepherd S, Glenny AM. Screening programmes for the early detection and prevention of oral cancer. Cochrane Database Syst Rev. 2013;(11):CD004150.
- Sankaranarayanan R, Ramadas K, Thara S, et al. Long term effect of visual screening on oral cancer incidence and mortality in a randomized trial in Kerala, India. Oral Oncol. 2013;49(4):314-21.
- Bhosale AS, Martins-Pfeifer C, Verdugo-Paiva F, et al. Living evidence-informed guideline on the early detection of oral squamous cell carcinoma and potentially malignant disorders: light-based adjuncts. J Am Dent Assoc. 2026;157(9):968-979.
- Urquhart O, Bhosale AS, Martins-Pfeifer C, et al. Living evidence-informed guideline on the early detection of oral squamous cell carcinoma and potentially malignant disorders: cytology adjuncts. J Am Dent Assoc. 2026;157(3):224-234.
- Walsh T, Warnakulasuriya S, Lingen MW, et al. Clinical assessment for the detection of oral cavity cancer and potentially malignant disorders in apparently healthy adults. Cochrane Database Syst Rev. 2021;12:CD010173.
- Walsh T, Macey R, Kerr AR, Lingen MW, Ogden GR, Warnakulasuriya S. Diagnostic tests for oral cancer and potentially malignant disorders in patients presenting with clinically evident lesions. Cochrane Database Syst Rev. 2021;7:CD010276.
- Iocca O, Sollecito TP, Alawi F, et al. Potentially malignant disorders of the oral cavity and oral dysplasia: a systematic review and meta-analysis of malignant transformation rate by subtype. Head Neck. 2020;42(3):539-555.
- Aguirre-Urizar JM, Lafuente-Ibáñez de Mendoza I, Warnakulasuriya S. Malignant transformation of oral leukoplakia: systematic review and meta-analysis of the last 5 years. Oral Dis. 2021;27(8):1881-1895.
- Idrees M, Kujan O, Shearston K, Farah CS. Oral lichen planus has a very low malignant transformation rate: a systematic review and meta-analysis using strict diagnostic and inclusion criteria. J Oral Pathol Med. 2021;50(3):287-298.
- González-Moles MÁ, Ramos-García P. An evidence-based update on the potential for malignancy of oral lichen planus and related conditions: a systematic review and meta-analysis. Cancers (Basel). 2024;16(3):608.
- National Institute of Dental and Craniofacial Research. Oral cancer.
- Hashibe M, Brennan P, Chuang SC, et al. Interaction between tobacco and alcohol use and the risk of head and neck cancer: pooled analysis in the International Head and Neck Cancer Epidemiology Consortium. Cancer Epidemiol Biomarkers Prev. 2009;18(2):541-50.
- Chaturvedi AK, Engels EA, Pfeiffer RM, et al. Human papillomavirus and rising oropharyngeal cancer incidence in the United States. J Clin Oncol. 2011;29(32):4294-301.
- Tota JE, Anderson WF, Coffey C, et al. Rising incidence of oral tongue cancer among white men and women in the United States, 1973-2012. Oral Oncol. 2017;67:146-152.
- Warnakulasuriya S, Kujan O, Aguirre-Urizar JM, et al. Oral potentially malignant disorders: a consensus report from an international seminar on nomenclature and classification. Oral Dis. 2021;27(8):1862-1880.
- American Dental Association, MouthHealthy. Oral cancer.
- Verdugo-Paiva F, Urquhart O, Bhosale AS, et al. Living evidence-informed guideline on the early detection of oral squamous cell carcinoma and potentially malignant disorders: salivary adjuncts. J Am Dent Assoc. 2026 (online ahead of print).
- Martins-Pfeifer C, Urquhart O, Verdugo-Paiva F, et al. Living evidence-informed guideline on the early detection of oral squamous cell carcinoma and potentially malignant disorders: vital staining adjuncts. J Am Dent Assoc. 2026;157(6):576-587.